
The Amulet™ 360 Left Atrial Appendage Occluder is available for sale in EUROPE.
Caution: investigational device. Limited by Federal (or United States) law to investigational use.
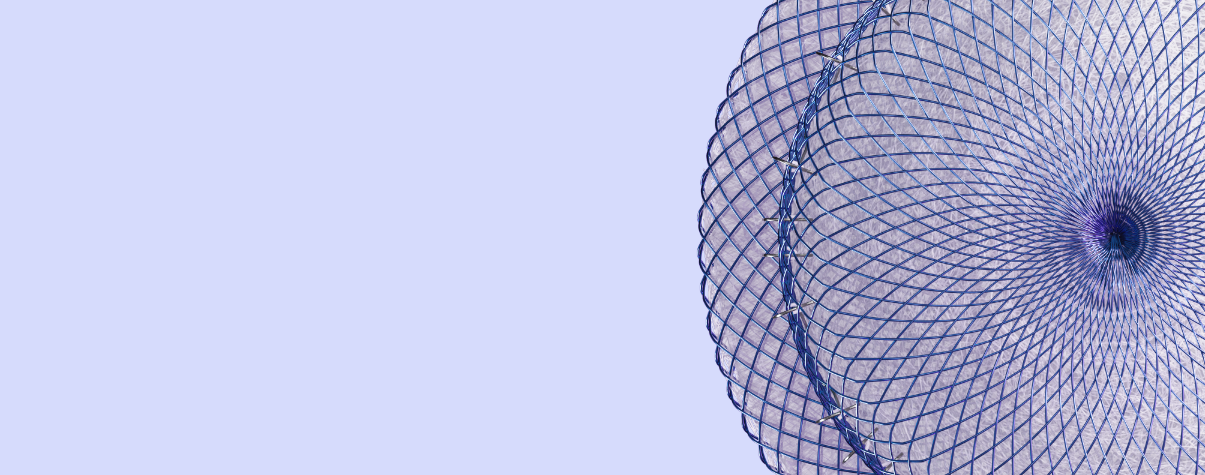
The Amulet™ 360 LAA Occluder is a dual-seal design made of two primary components.
- A conformable lobe that fills and closes the appendage
- A disc that creates a seal at the LAA ostium
CLEAR Concomitant Study: Early safety and effectiveness results of Abbott PFA and LAAO procedure1
CLEAR is a prospective multicenter study evaluating the feasibility, safety, and effectiveness of a concomitant procedure with Volt PFA for atrial fibrillation (AF) treatment and LAA occlusion with next-generation dual-seal device, Amulet 360. Study subjects are patients with non-valvular AF who are indicated for both AF ablation and LAA occlusion (LAAO) and were released on a standardized post-procedure OAC regimen at discharge.
This early experience in the first 68 patients of the study, presented at APHRS 2026, provides insights into feasibility of a standardized concomitant workflow.
7-day Safety
0%
Primary safety event rate
No death, ischemic stroke, systemic embolism, or device/procedure-related complication requiring major intervention
Procedural Findings:
100%
- Acute PV Isolation Success with Volt PFA system
- Amulet 360 Left Atrial Appendage Occluder Implant Success
n=68/68
Average Procedure Time & Sedation Workflow
51.7 minutes (± 22.1)
Procedure time reported as Access-to- venous close, including PV Isolation and LAA Closure
37%
Of procedures completed without General Anesthesia
Closure: In procedure
100%
Acute Complete Closure (0mm leak)
Including in patients with
Complex LAA morphology
(72% chicken wing or multi-lobe)
The VERITAS Study
The VERITAS Study2: early outcomes (45-day)
First results from the VERITAS Study were presented at AF Symposium 2026, providing the earliest clinical evidence evaluating the Amulet™ 360 LAAO* in patients with nonvalvular AF. The findings show that both primary endpoints were met with statistically significant performance, supported by independent core lab review.
Study outcomes
Early findings from the VERITAS Study, provided the first data on the safety, effectiveness, and early closure performance for the Amulet™ 360 LAAO*.
Safety and effectiveness endpoints
0%
p < 0.0001 (n=40/400)
Primary safety endpoint**
(performance goal: 3.75%)
100%
p < 0.0001 (n=396/396)
Primary effectiveness***
endpoint (performance goal: 96.6%)
Closure assessment at 45-days: independent core lab observe
100%
Clinically relevant closure (no PDL >3mm identified)
93.9%
Complete closure (0mm leak) on 45-day follow up TEE
Procedural metrics
99.8%
Implant success
88%
Of subjects implanted with a single device attempt
0.5%
Pericardial effusion requiring drainage
0%
Device embolization
* Previously reported data.
** Primary safety endpoint was key adverse events (death, ischemic stroke, systemic embolism, or device/procedure related complications requiring open cardiac surgery or major endovascular Intervention) through 7 days post-procedure or hospital discharge, whichever was later.
***Primary effectiveness endpoint: LAA occlusion defined as no peri-device flow or peri-device flow ≤ 5 mm based on Doppler color flow TEE at the 45-day follow-up visit as assessed by an independent core laboratory.
Impact of procedural experience of a next generation LAAO device - insights from the VERITAS Study3
Key takeaways
- 100% implant success after implanters 5th case
- Complete closure (0 mm leak) in majority of cases, from roll-ins (84.3%) to experienced users, defined as those with 5+ procedures (96.1%)
- Procedural time decreased with implanter experience


100%
Peri-device leak ≤3 mm regardless of experience
96.1%
Complete closure (0 mm leak) in experienced group


The Amulet™ 360 Left Atrial Appendage Occluder is available for sale in EUROPE.
Caution: investigational device. Limited by Federal (or United States) law to investigational use.
- Nair, D, Reddy, V, et al. Concomitant Balloon-in-Basket Pulsed Field Ablation and Next-Generation Left Atrial Appendage Occlusion: First Results from the ProspectiveMulticenter CLEAR study, EP Europace, Published online October 2026. https://www.doi.org/10.1093/europace/euag299
- Nair, D., Freixa, X., Ellis, C. R., Lakkireddy, D., Nielsen-Kudsk, J. E., Horton, R., Reddy, V. Y., & the VERITAS Investigators. (2026). Early outcomes with a next-generation dual-seal left atrial appendage occluder: Results from the VERITAS study. JACC: Clinical Electrophysiology, 12(6).
- Nair D, Lakkireddy, D, Alkhouli, M, et al. Impact of Procedural Experience of a Next Generation Left Atrial Appendage Occlusion Device – Insights from the VERITAS Study. Presented by Dr. Devi Nair at NY Valves; June 26, 2026; New York, NY USA.
Rx Only. Brief Summary: Prior to using these devices, please review the Instructions for Use for a complete listing of indications, contraindications, warnings, precautions, potential adverse events, and directions for use.
United States: Required Safety Information
Indications for Use: The Volt™ PFA Catheter, Sensor Enabled™ is indicated for the treatment of symptomatic, recurrent, drug-refractory paroxysmal or persistent (episode duration less than one year) atrial fibrillation when used in conjunction with a compatible pulsed field ablation (PFA) generator. The catheter is compatible with the EnSite™ X EP System. Contraindications: The Volt™ PFA Catheter, Sensor Enabled™ is contraindicated for: ▪ Patients who have had a ventriculotomy or atriotomy within the preceding four weeks. ▪ Patients with prosthetic valves as the catheter may damage the prosthesis. ▪ Patients with an active systemic infection as this may increase the risk for cardiac infection. ▪ Patients with a myxoma or an intracardiac thrombus as the catheter could precipitate an embolus. ▪ Patients unable to receive heparin or an acceptable alternative to achieve adequate anti-coagulation. The transseptal approach is contraindicated in a patient with an interatrial baffle or patch because the opening could persist and produce an iatrogenic atrial shunt. The retrograde trans-aortic approach is contraindicated in patients who have had aortic valve replacement. Warnings: Misuse of this device may result in serious complications. Do not alter this device in any way. This device is intended for one time use only; do not reprocess or reuse it. Note the product “Use by” date on the package. Any attempt to resterilize and reuse this system may compromise its integrity. Adverse effects of using nonsterile components may include, but are not limited to: ▪ Local or systemic infection or reaction ▪ Mechanical damage ▪ Inaccurate functionality. For both patients and laboratory staff, cardiac catheterization procedures present the potential for significant x-ray exposure, which can result in acute radiation injury as well as increased risk for somatic and genetic effects due to the x-ray beam intensity and duration of the fluoroscopic imaging. Carefully consider the use of this device in pregnant women. This device should be used by physicians trained in the techniques of catheter ablation in a fully equipped electrophysiology laboratory. Do not immerse the proximal handle or cable connectors in fluids; electrical performance could be affected. Do not use excessive force to advance or withdraw the catheter when resistance is encountered. Vascular perforation or dissection is an inherent risk of any catheter placement. Careful catheter manipulation must be performed to avoid device component damage, thromboembolism, cerebrovascular accident, cardiac damage, perforation, pericardial effusion, or tamponade. The safety and long-term effects of lesions created by pulse field ablation have not been established. In particular, the long-term effects of lesions in proximity to the specialized conduction system or coronary vasculature are unknown. The safety and effectiveness of the device has not been established in pregnant women or pre-pubescent children. Careful consideration must therefore be given for the use of the device in pregnant women or prepubescent children. Concurrent use of non-linear catheters within the atrial chamber may increase the risk of entanglement. Catheter entanglement with other device is a possible complication of electrophysiology procedures. To unentangle the Volt™ PFA Catheter, Sensor Enabled™, deflate the balloon and manipulate the opposing catheter to the center of the basket electrodes. Follow any relevant entanglement procedures from the opposing device. Aspiration during catheter introduction or withdrawal is recommended to limit the potential for air ingress into the patient. During catheter preparation, rinsing or submerging the basket in saline reduces the potential for blood coagulation. During catheter preparation, shifting the straightener over the basket removes any residual air remaining in the folds of the balloon and reduces the potential for air embolism. Use of a syringe larger than 12 mL for balloon inflation increases the risk of overinflation. This can result in detachment of the spline electrodes at the distal coupler. Pacemakers and implantable cardioverter/defibrillators can be affected adversely by PFA signals. It is important to: ▪ Have temporary external sources of pacing and defibrillation available during ablation. ▪ Deactivate ICDs because they can discharge and injure the patient or even damage the ICDs during the ablation procedure. ▪ Exercise extreme caution while ablating near atrial or ventricular permanent pacing leads. ▪ Perform complete pacing system analysis on all patients after ablation. Precautions: Do not deflect the introducer while the basket is within the deflectable portion of the introducer, as this can cause damage to the introducer deflection mechanism. Do not deflect the Volt™ PFA Catheter, Sensor Enabled™ while the basket is in the introducer, as this can cause damage to the catheter deflection mechanism. The first application of PFA will likely result in a significant reduction of amplitude of PV potentials recorded from the electrodes on the catheter. Do not use this as an immediate indication that no further ablation is necessary. The PFA therapy should be delivered in accordance with the Therapy Delivery Parameters. Advance the catheter slowly through the introducer to minimize the risk of air embolism. Do not attempt to use the device before completely reading and understanding the applicable instructions for use. Inspect the package prior to use. Do not use if the packaging or catheter appears damaged. Inspect all components before use. Excessive bending or kinking of the catheter may cause damage to the catheter. Be careful not to twist the electrodes with respect to the catheter shaft; twisting may damage the electrode bond and loosen the electrodes. Release the steering (make the catheter straight) prior to pulling back the catheter into the introducer. Deflate the balloon before pulling the catheter back into the introducer. Overinflation of the balloon may cause damage to the device. Always straighten the catheter shaft and keep the balloon deflated before insertion or withdrawal. Do not use if the catheter appears damaged, kinked, or if there is difficulty in deflecting the distal section to achieve the desired curve. Do not use if the catheter does not hold its curve or if there is difficulty deflecting the catheter. Do not use if there is difficulty inflating or deflating the balloon. Do not use excessive force to advance or withdraw the catheter while inside the introducer when resistance is encountered to avoid potential damage to the catheter. Do not expose catheter to organic solvents such as alcohol. Catheter advancement must be performed with support from visualization modalities such as Intracardiac echo, fluoroscopy, and or compatible navigation and visualization systems to minimize the risk of cardiac damage, perforation, or tamponade. If other catheters are used concomitantly with the Volt™ PFA Catheter, Sensor Enabled™, only use other catheters in close proximity when the balloon is inflated, and never in tandem with the catheter in the same pulmonary vein. Never retract the catheter into the introducer when another catheter is in close proximity. Never use a loop catheter concomitantly with the Volt™ PFA Catheter, Sensor Enabled™ within the same atrial chamber. Retract the catheter into the introducer before using a loop catheter within the same chamber. Prior to therapy delivery, ensure that the guidewire is not touching the basket electrodes to prevent ineffective therapy. Compliance with intended therapy delivery parameters reduces the potential for hemolysis and acute kidney injury. Ensure that vacuum pressure is relieved and balloon is fully deflated. After deflating the balloon, leave the stopcock open between the syringe and the inflation lumen to prevent catheter damage during catheter withdrawal. It is recommended to withdraw the guidewire into the introducer prior to balloon deflation to avoid potential entanglement with spline electrodes. Ensure even spacing for splines and full balloon inflation to reduce potential for generator fault detection. Ensure connection to center lumen stopcock when attempting to inject contrast. The balloon inflation lumen has a blue/grey striped sleeve to visually distinguish it from the center lumen stopcock. Do not touch the guidewire during therapy delivery. Risk of electric shock to the user is possible under rare circumstances in which the guidewire is in contact with an active therapy electrode(s) and the user. During treatment with the catheter, ensure there is no possibility of contact with electrodes from another catheter. To avoid thromboemboli, intravenous heparin should be used when entering the left heart during ablation. Consult the HRS consensus guidelines for anticoagulation strategies pre-, during, and post-catheter ablation. Individual patient anatomy and physician technique may require procedural variations. Maintain an activated clotting time (ACT) of greater than 300 seconds at all times during use of the catheter. Store in a dry place. After use, the device accessories and packaging should be appropriately classified for disposal, e.g. biohazard, sharps, non-hazardous waste etc., and carefully disposed of in compliance with facility procedures and applicable laws and regulations. Catheter materials are not compatible with magnetic resonance imaging (MRI). Potential Adverse Events: The potential adverse events may be related to the ablation catheter(s) and/or the interventional procedure. The severity and/or the frequency of these potential adverse events may vary and may result in prolonged procedure time and/or additional medical and/or surgical intervention, implantation of a permanent device such as a pacemaker, and in rare cases, may result in death. The following adverse events have been documented for catheter ablation procedures: ▪ Abnormal vision ▪ Acute kidney injury ▪ Air embolism ▪ Anesthesia reaction ▪ Angina/chest pain/discomfort ▪ Aorto-right atrial fistula ▪ Arrhythmias, including exacerbation of preexisting atrial fibrillation ▪ Arteriovenous fistula ▪ AV/SA node stunning (asystole) ▪ Bleeding, including major bleeding requiring surgery or transfusion/hematomas/anemia ▪ Cardiac perforation/tamponade ▪ Cardiac embolism ▪ Cardiovascular injury, including atrial trauma and coronary artery/pulmonary vein trauma ▪ COPD exacerbation ▪ Component damage to Implantable Cardioverter Defibrillator(ICD) or implantable pacemaker ▪ Coronary artery spasm ▪ Cytotoxicity/systemic toxicity/sensitization/endotoxin/pyrogen ▪ Death ▪ Dislodgement of ICD or pacing leads ▪ Electrical shock ▪ Endocarditis ▪ Esophageal lesion ▪ Fever ▪ Foreign body embolism ▪ Heart block/unintended ablation ▪ Heart failure ▪ Hemothorax ▪ Hypotension ▪ Infectious pericarditis ▪ Left atrial esophageal fistula ▪ Myocardial infarction ▪ Neck/back/groin/chest pain/discomfort (general chest pain not associated with MI) ▪ Palpitations ▪ Pericarditis ▪ Pericardial effusion ▪ Phrenic nerve injury ▪ Peripheral vascular dissection/laceration ▪ Pleural effusion ▪ Pneumonia ▪ Pneumothorax ▪ Pseudoaneurysm ▪ Pulmonary edema ▪ Pulmonary embolism ▪ Pulmonary hypertension ▪ Pulmonary vein stenosis ▪ Radiation injury ▪ Respiratory failure/distress/depression/hypoxia ▪ Silent cerebral event/lesion ▪ Stiff Left Atrial Syndrome ▪ Stroke/cerebrovascular accident ▪ Syncope/vasovagal reaction/dizziness ▪ Transient ischemic attack (TIA) ▪ Thromboembolism ▪ Thrombosis/thrombus ▪ Vagal nerve injury including Gastroparesis ▪ Valvular damage or insufficiency.
MAT-2623454 v5.0