
TactiFlex™ Duo Ablation Catheter, Sensor Enabled clinical evidence : Atrial Ablation
The PFA components of the system consist of the following:
- TactiFlex™ Duo Ablation Catheter, Sensor Enabled™: A dual energy, flexible-tip focal ablation catheter that can transmit either RF energy or PFA therapy. It is designed for therapy delivery, pacing, and collection of electrical and anatomical data when used with the EnSite™ X EP System.
- Current™ PFA Generator: The streamlined user interface includes energy source selection and PFA waveform selection. Abbott’s Current PFA Generator is designed for intuitive use and can also be used with the Volt™ PFA Catheter, Sensor Enabled™.
The RFA components of the system consist of the following:
- Ampere™ RF Generator
- CoolPoint™ Pump
- TactiSys™ Quartz Equipment
Explore the data
Key clinical trials
Procedural factors associated with 12-month effectiveness12
A pooled analysis of the FOCALFLEX and FlexPulse clinical studies evaluated associations between procedural factors and 12-month effectiveness of a dual energy RF/PF ablation system for paroxysmal atrial fibrillation.
Standard of Care Monitoring
93.8%
Freedom from Documented AF/AFL/AT Recurrence at 12 months
Strict Monitoring with protocol-specified TTM, ECG, Holter Monitor
73.7%
Freedom from documented AF/AFL/AT recurrence at 12 months from protocol-specified TTM, ECG
When PI + AMD workflow is used
85.7%
Freedom from documented AF/AFL/AT recurrence with Strict Monitoring (n=48/56)
19%

Increase in freedom from documented AF/AFL/AT
recurrence with HD Grid (versus a CMC)
Effectiveness was not impacted by:
(p>0.05)
Fluoroscopy use
Sedation type
PV anatomy
Above median BMI
Above median CHA₂DS₂-VASc
Biological sex
FlexPulse IDE 12-month results1
The FlexPulse IDE study describes the use of a dual-energy (pulsed field ablation and radiofrequency) system in patients with PAF treated with PVI, with additional ablation beyond PVI permitted when clinically indicated.
Safety
1.7%
Primary safety event rate1
0%
Stroke/TIA, phrenic injury, esophageal lesions, pulmonary vein stenosis, device and/or procedure related deaths reported1
Efficacy
92.6%
Freedom from AF/AFL/AT recurrence with standard of care monitoring
91.7%
Freedom from repeat ablation at 12 months* n=165/1801
74.6%
Freedom from any primary effectiveness endpoint events1
*Post 90-day blanking period and through 12 months
Workflows
93%
PFA Only PVI
53%
Same day discharge
28%
Zero Fluoroscopy
Demographics
 24
Sites worldwide
 180
Paroxysmal AFib patients treated worldwide
FOCALFLEX CE Mark study
6-month data evaluated safety and effectiveness in a range of conditions2
Recent results from the FOCALFLEX Study describe the use of the TactiFlex Duo System in pulsed field ablation procedures and outline observations related to safety data and ablation approaches evaluated in the study.
1.4%
Primary safety event rate (n=2/147)2
0%
Of subjects reporting phrenic nerve injury, PV stenosis, death, or esophageal injury2
81%
Of patients remained free from documented arrhythmia recurrence at 6 months (AF/AFL/AT)2
1
Repeat ablation* (1/144)2
99.6%
Acute effectiveness per vein* (565/567)2
94.2%
First-pass isolation per vein** (534/567)2

Demographics
21
Centers in Australia and Europe
144
Patients treated: Mean age 62 ± 10 years 63% male

Ablation protocol PFA on the posterior wall RF on regions adjacent to coronary arteries
Workflow: PFA Index for PF applications
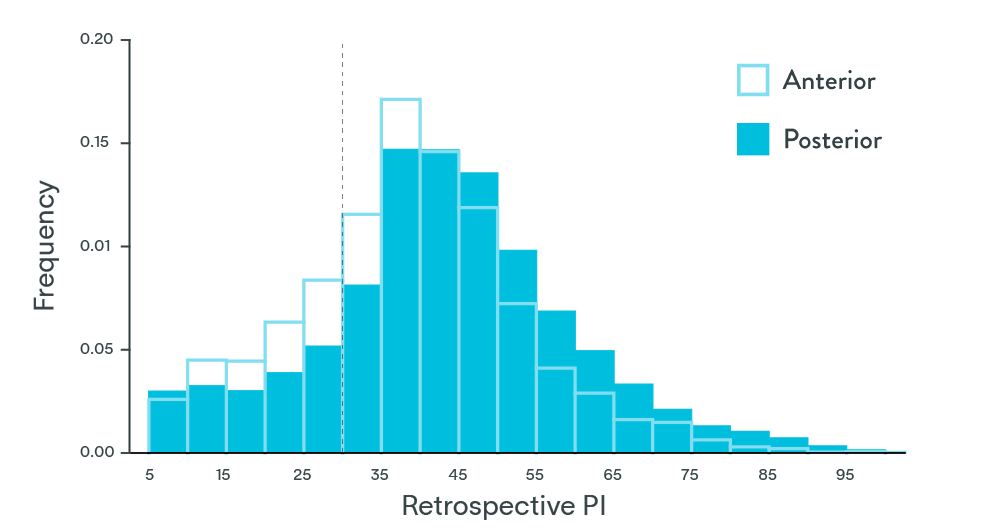
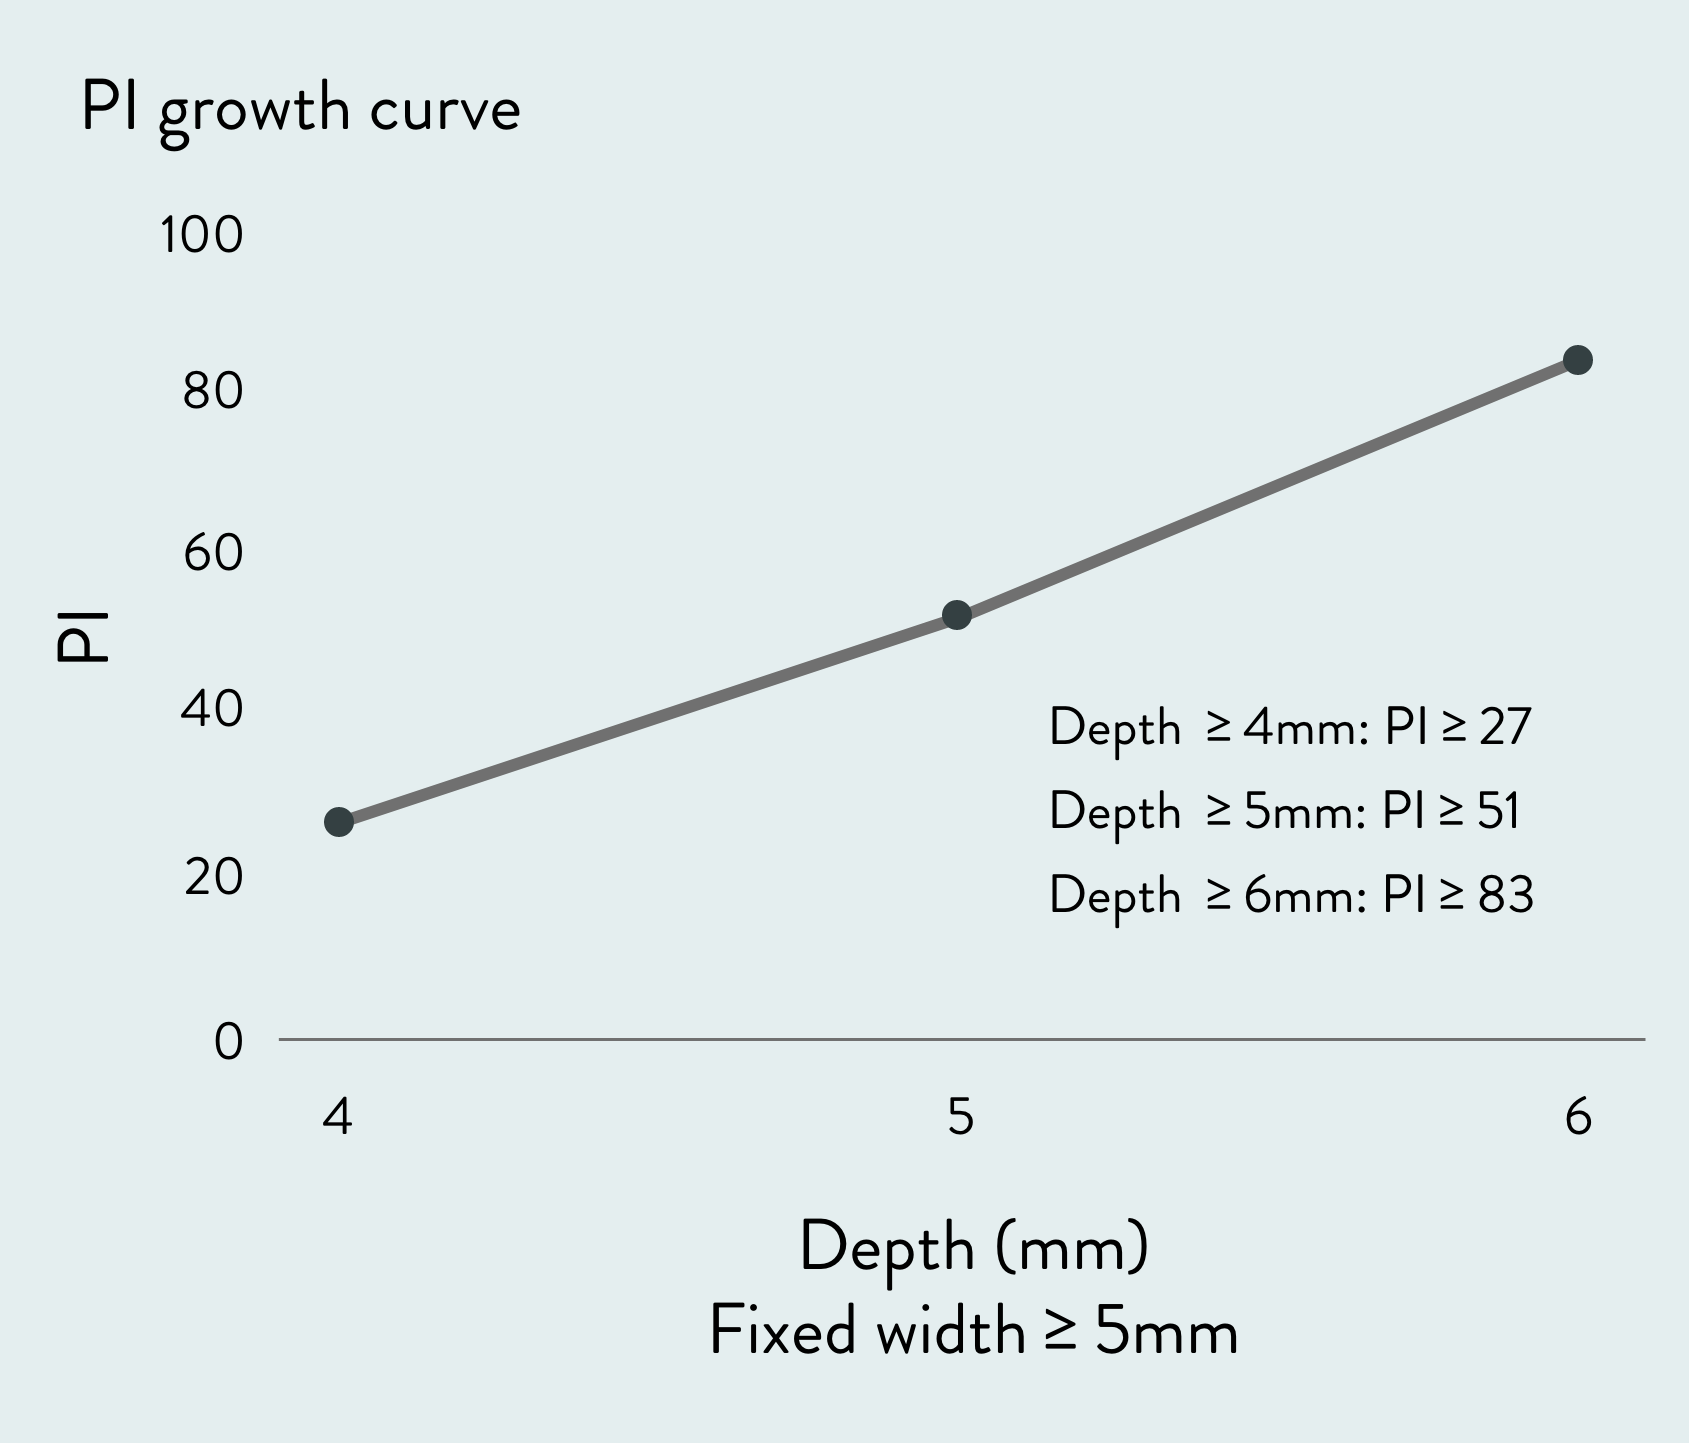
The TactiFlex Duo system includes a PFA Index (PI), a real-time integration of factors associated with lesion formation that measures the therapy effect of PFA energy delivery. These factors include sufficient energy delivery, tissue contact, and local tissue response. The PI metric can be used as an additional tool for indication of lesion progression during PF energy delivery.
Impact of PFA Index: Retrospective Analysis of IDE trial 1
Initial insight into threshold values of a novel PFA Index and AutoMark Distance using a dual-energy RF/PF ablation catheter that are positively associated with freedom from arrhythmia recurrence at 12 months after ablation with a dual-energy catheter.
84.6%
Freedom from documented AF/AFL/AT
at 12-months in cases where
- 80% of lesions with PI values of ≥ 30
- 90% of lesions with Automark Distance ≤ 6mm
Prospective, real-world use of the PFA Index Metric13
This multi-center collaboration evaluated alignment in real-world use and the Duo workflow with demonstrated clinical success from the IDE in a retrospective analysis.
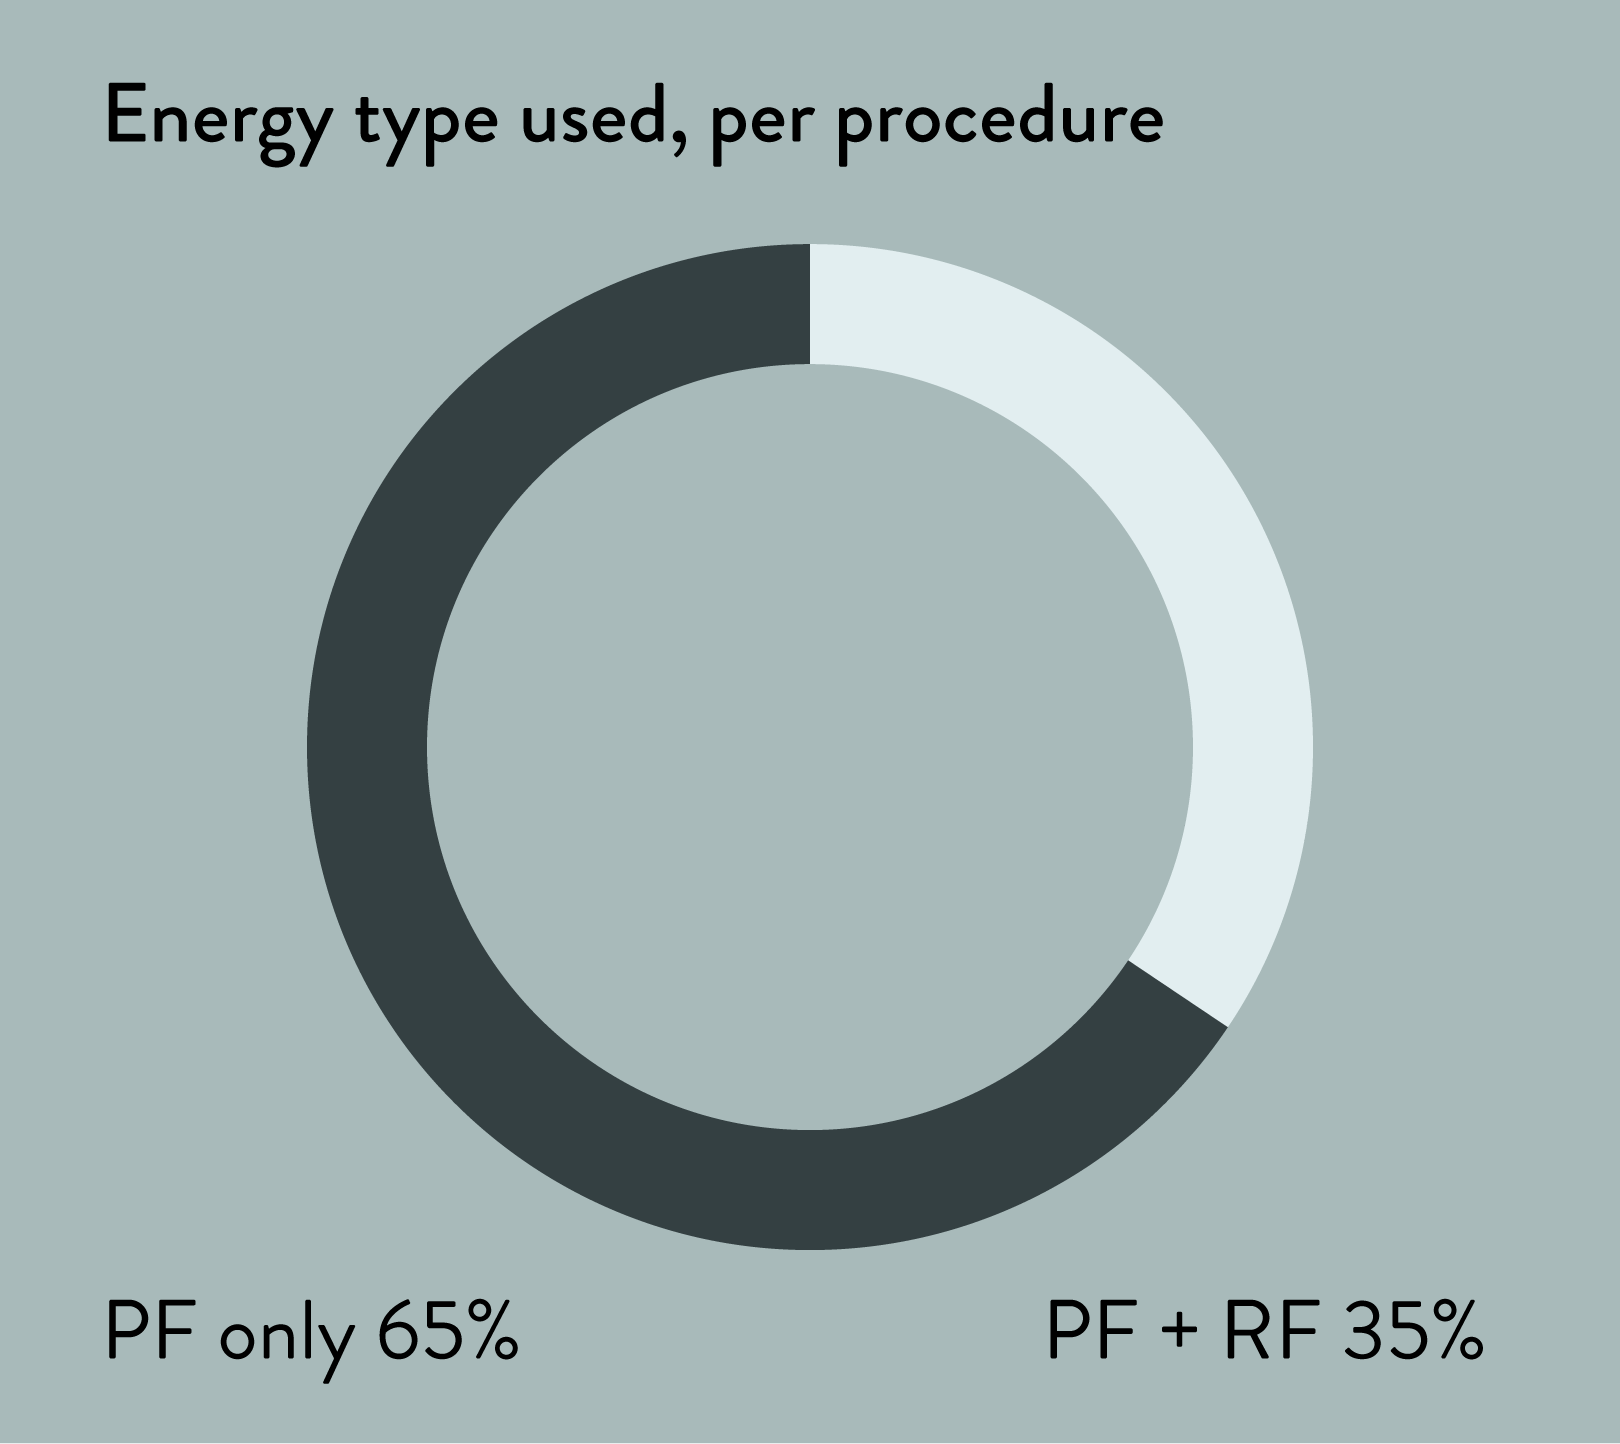
PVI and linear applications were both applied and were acutely successful with PF only in majority of procedures.
92%
Of cases had average PI value > 30 and average AMD up to 6mm*
*current suggested atrial thresholds
98%
Acute success
Development of PFA Index9
In animal studies, numerous factors were tested for impact on PFA Lesion progression.
Top impacting factors:
- Number of bursts delivered for sufficient energy
- % Time contact force ≥ 5 g for sufficient tissue contact
- Change in local bipolar tissue impedance (D-2) for local tissue response
Workflow: AutoMark Index for RF applications
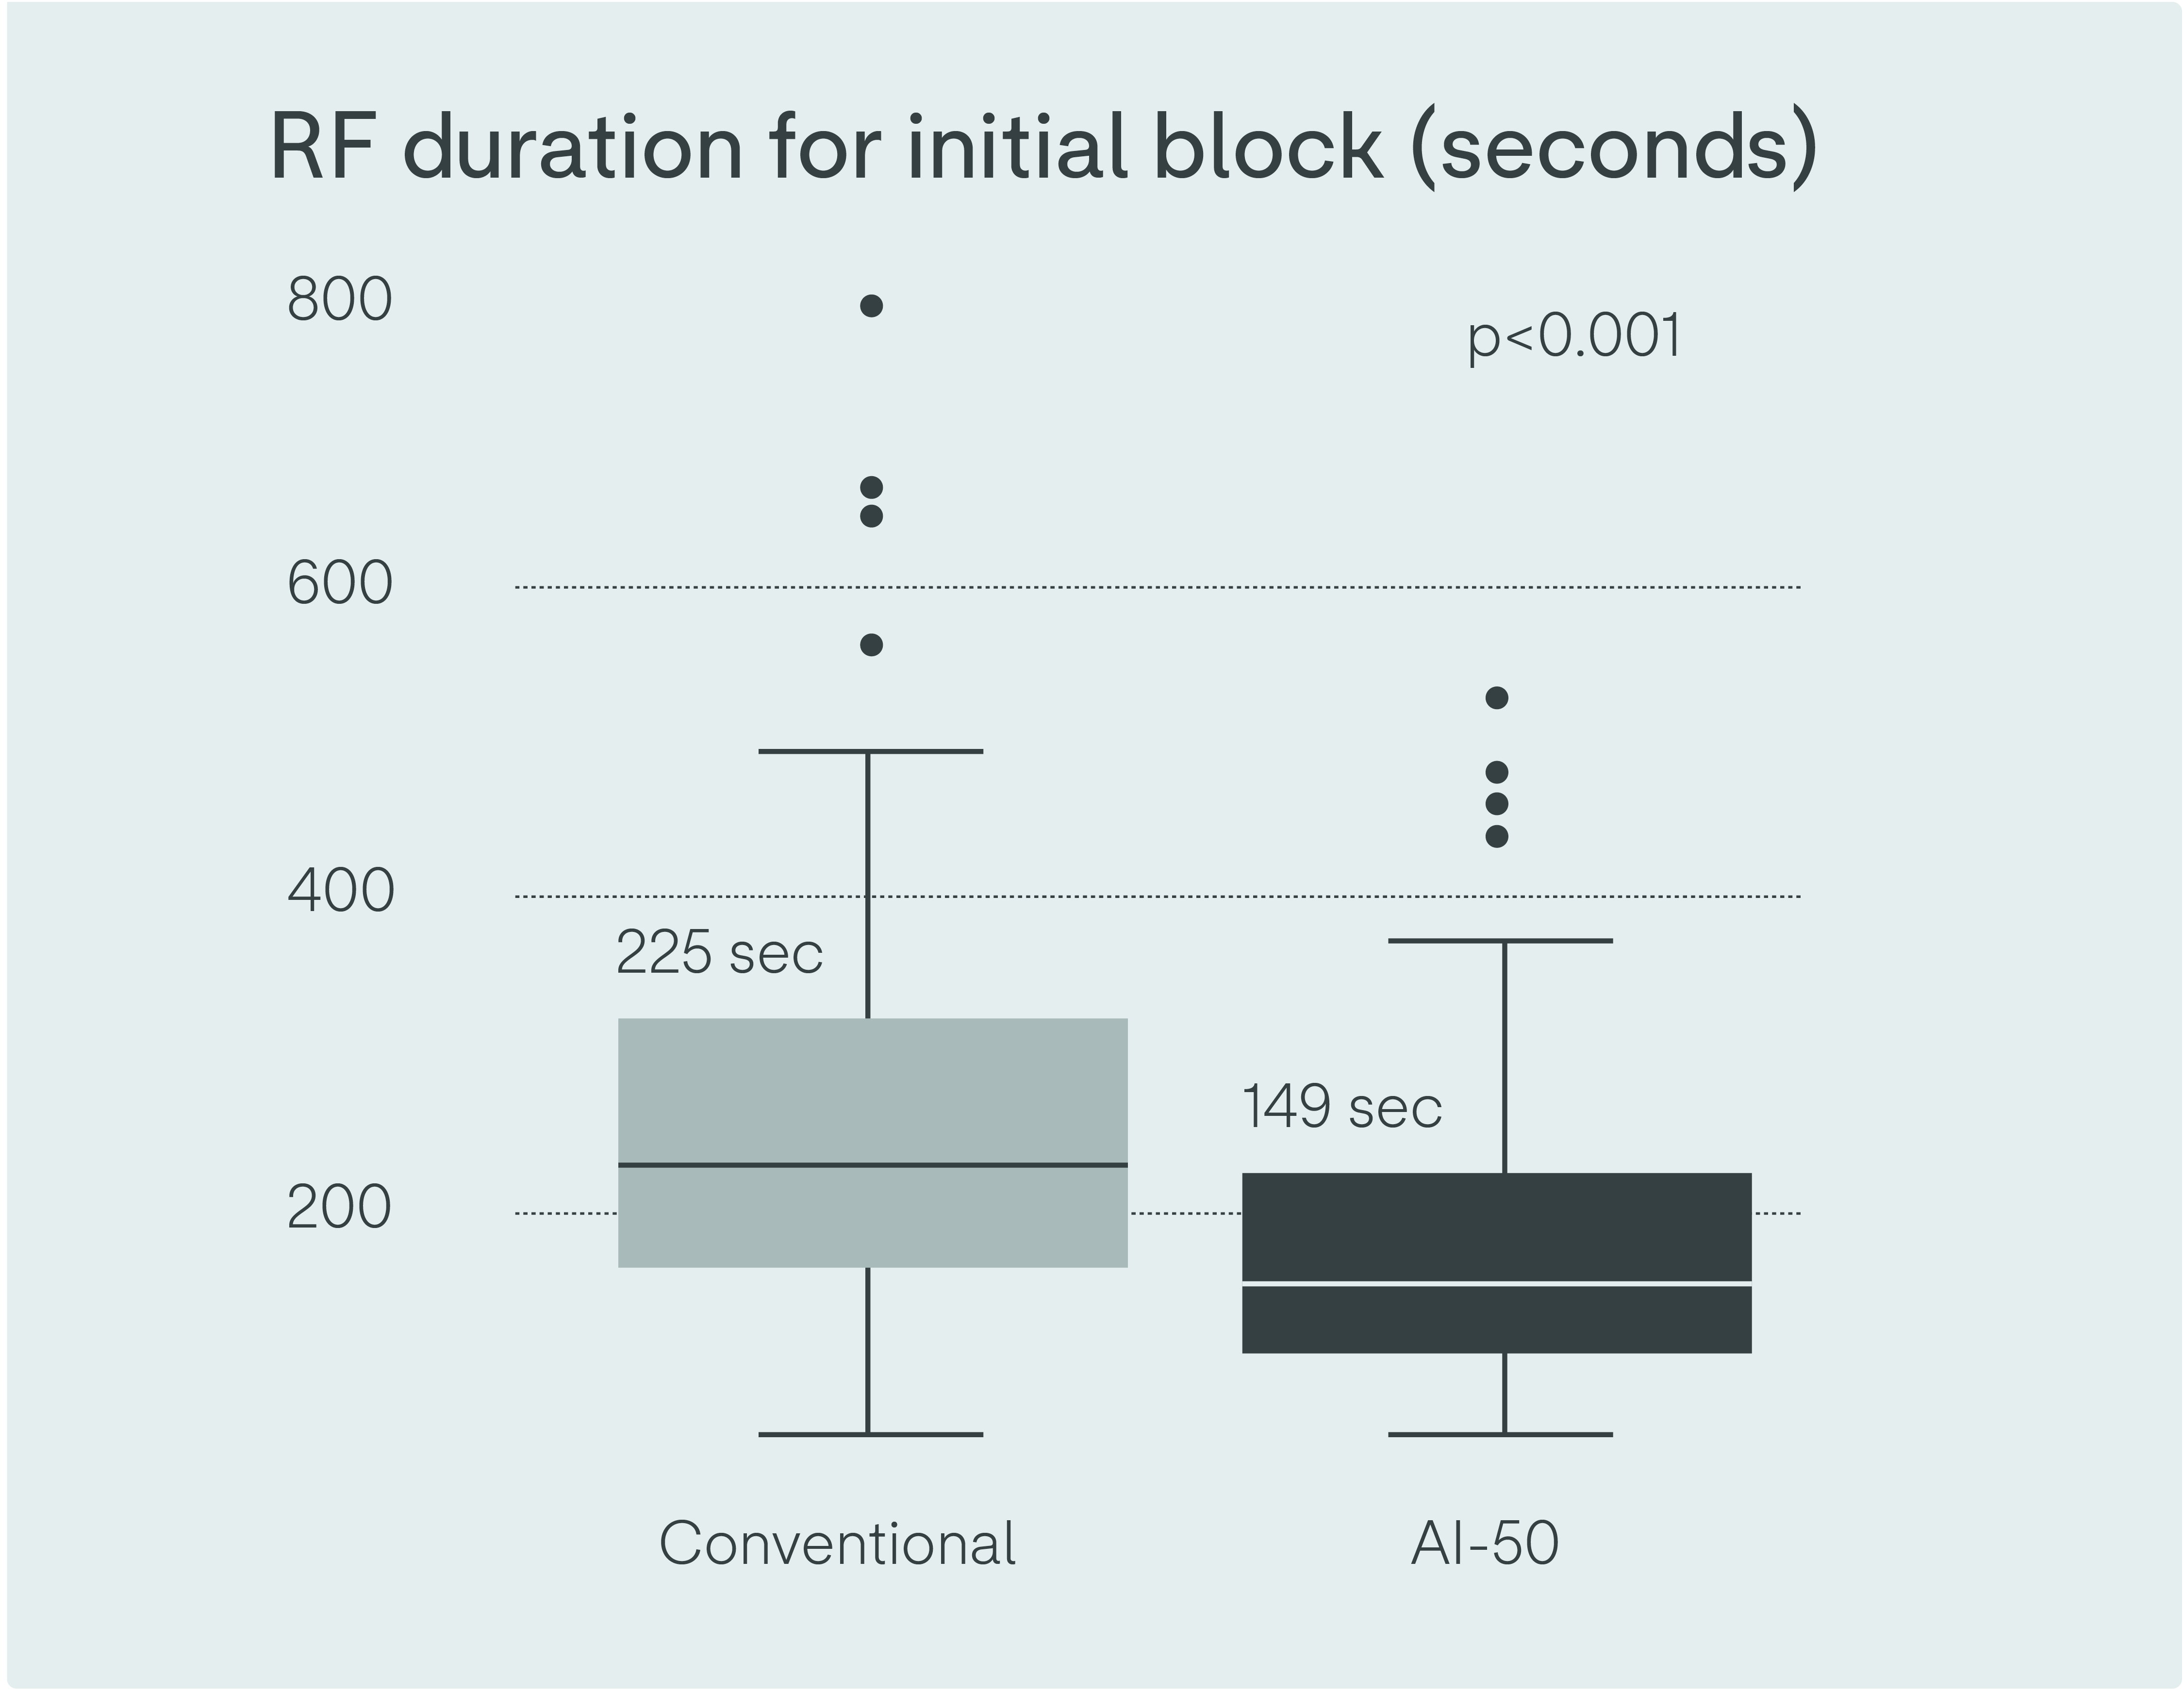
The TactiFlex™ Duo catheter offers both PFA and RFA delivery options. For clinical situations in which RFA is most appropriate, the AutoMark Index (AI) can be used as an indicator for lesion progression during energy delivery. AutoMark Index (AI) is a real‑time summary metric of three RF ablation parameters: Contact Force, RF Current, and RF application duration.
AutoMark Index-Guided CTI Ablation: Efficacy, efficiency, and safety11
Efficient RF delivery with acute efficacy and favorable safety profile.
In a single-center study of 148 consecutive patients, CTI ablation using the TactiFlex™ catheter was completed.
Two cohorts were evaluated. One group (AI-50) used a target AutoMark Index (AI) of 50, while the second group (Conventional) used a 40W, 20-second protocol. The AI-50 group achieved 100% acute bidirectional block while reducing total RF duration compared with the conventional group.
Workflow: sedation & beyond PVI3
Across both the FOCALFLEX and FlexPulse trials, sedation strategy was left to operator discretion, demonstrating the flexibility of TactiFlex™ Duo across a range of workflow preferences, including general anesthesia, conscious sedation, and deep sedation.
Sedation workflows in clinical trials3
FOCALFLEX CE Mark2
Sedation Method
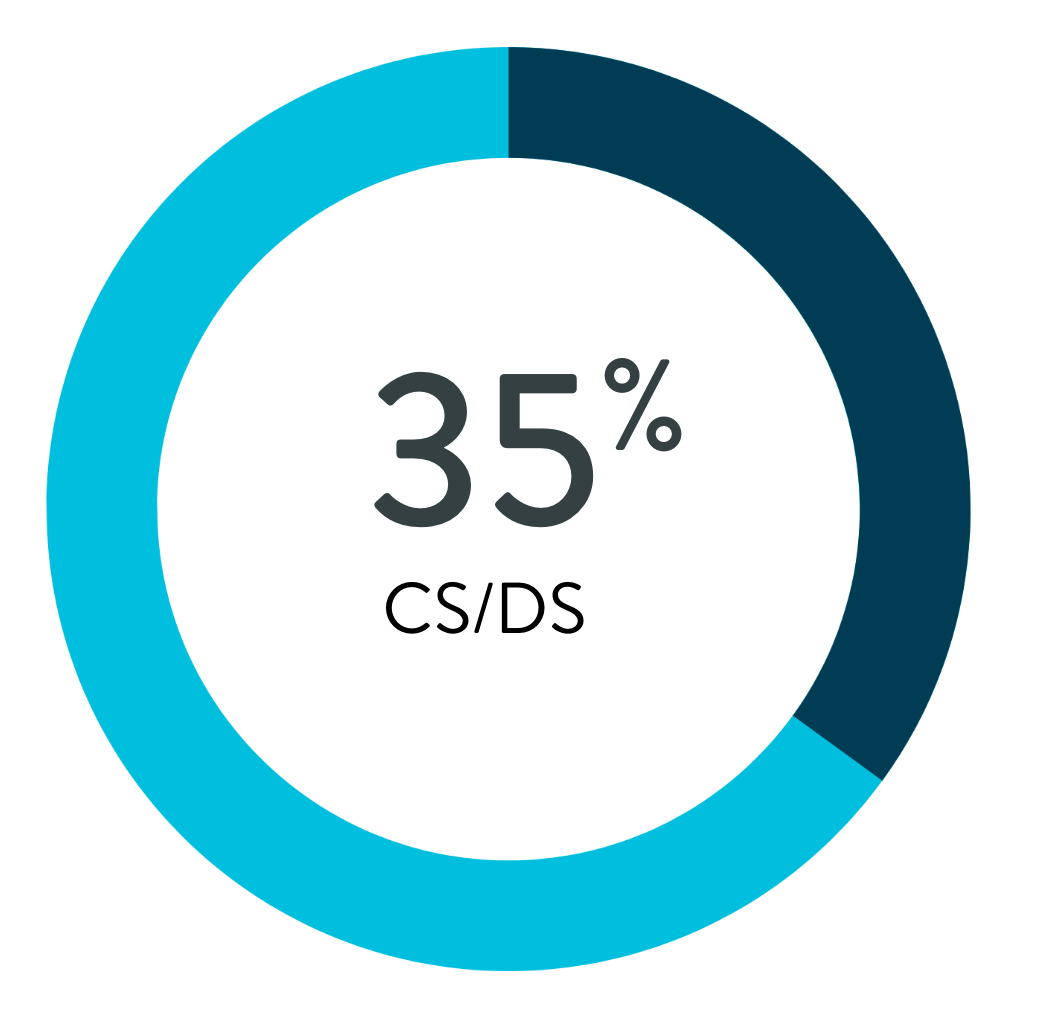
65% General Anesthesia
FlexPulse IDE1
Sedation Method
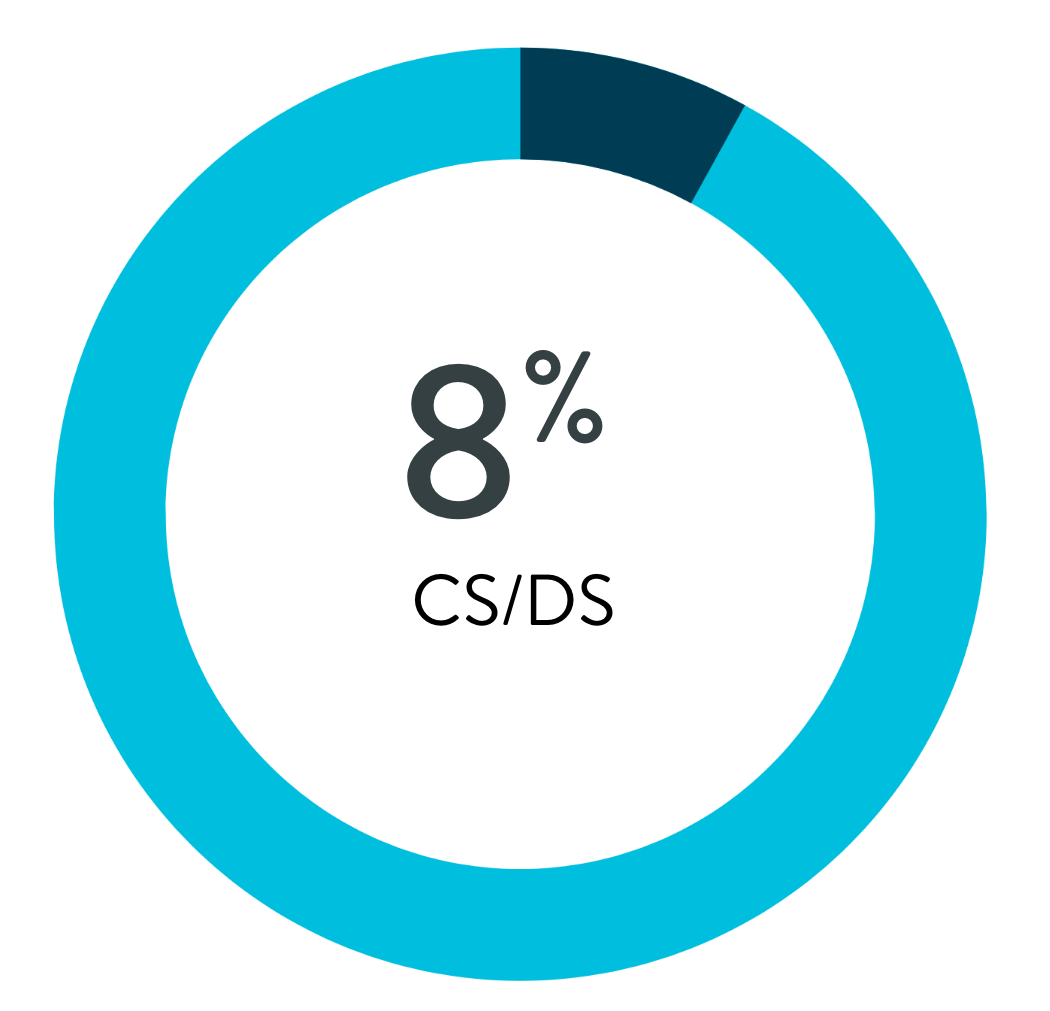
92% General Anesthesia
Proportion with none or clinically acceptable SMR as defined by operator
92.8% GA cases
92.9% DS cases
Clinical trial beyond PVI findings4
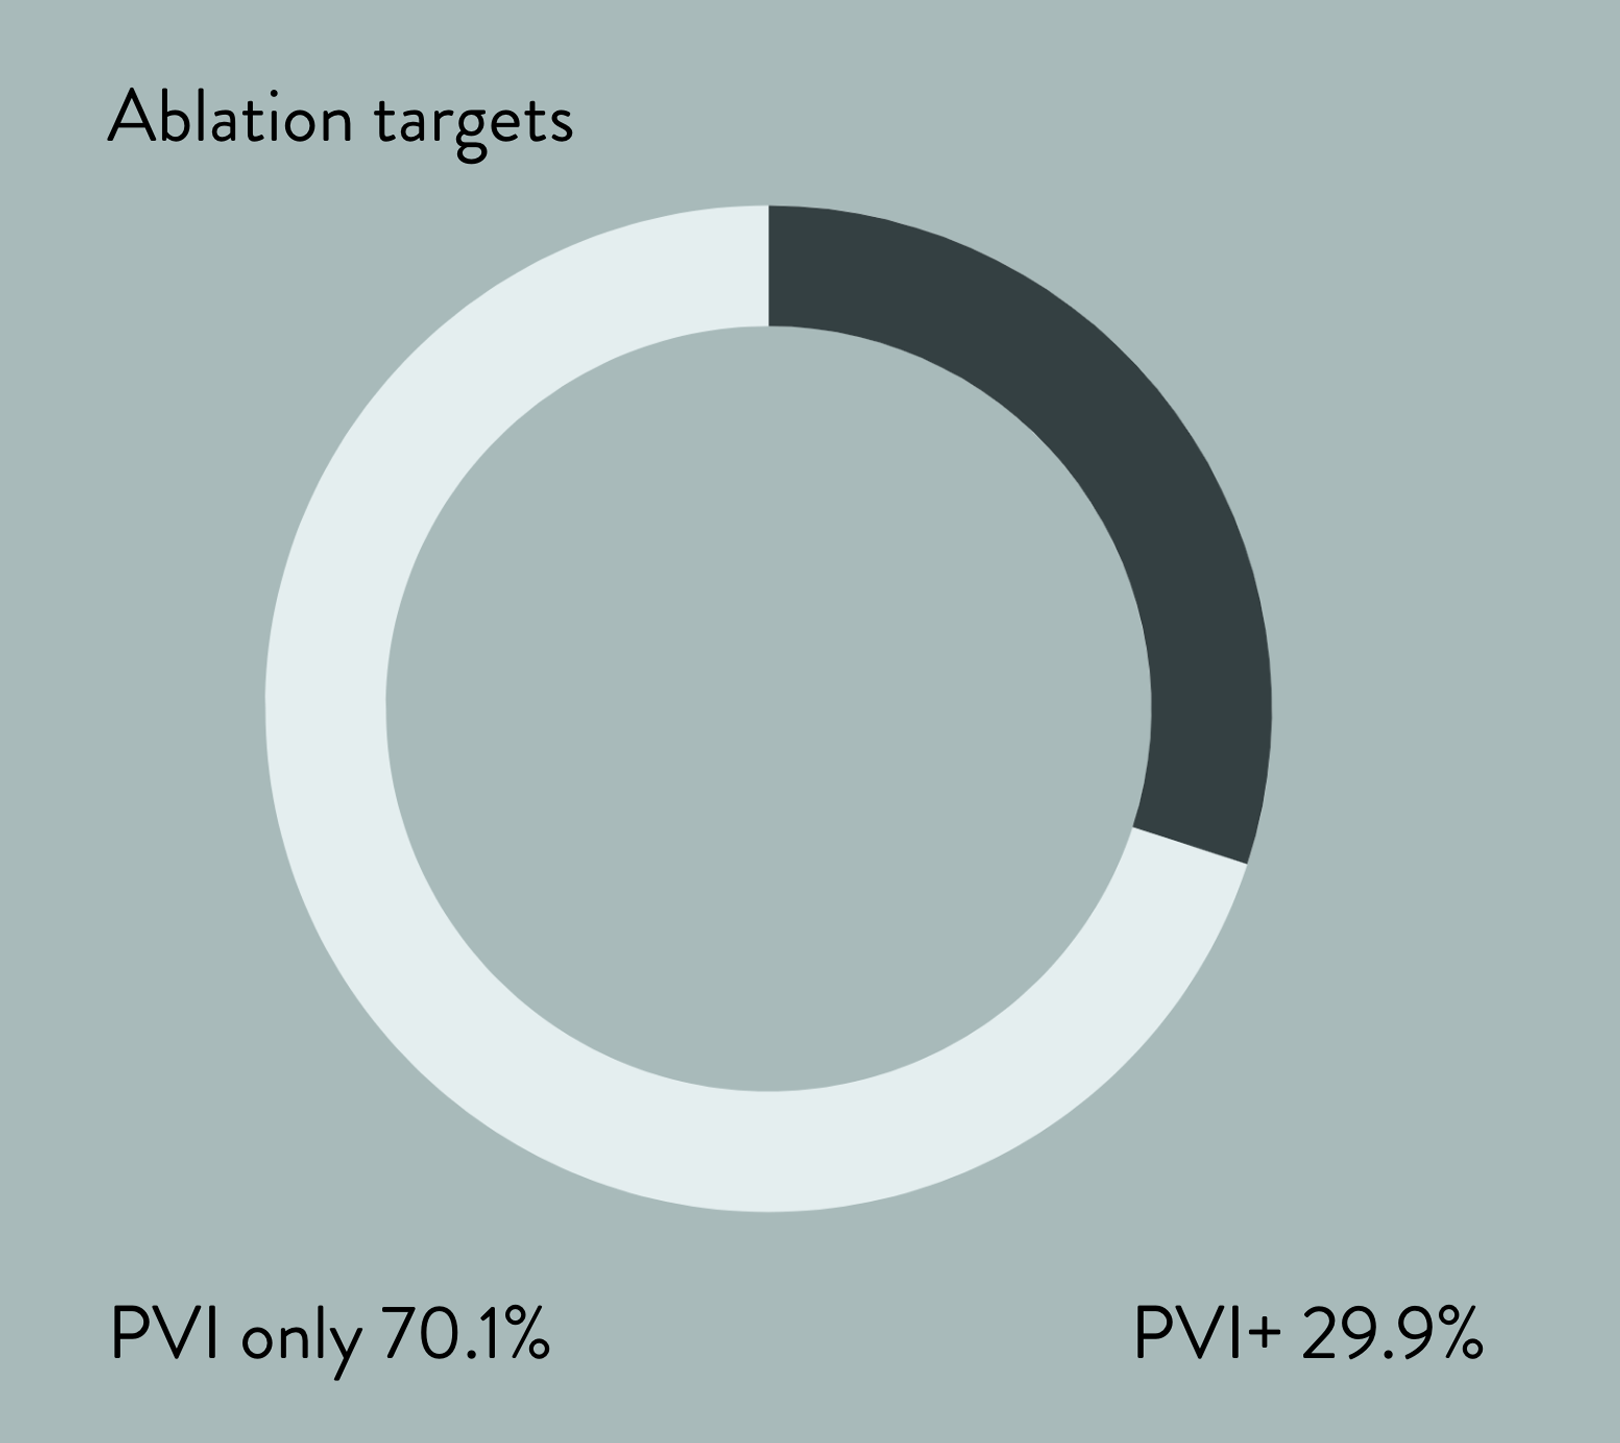
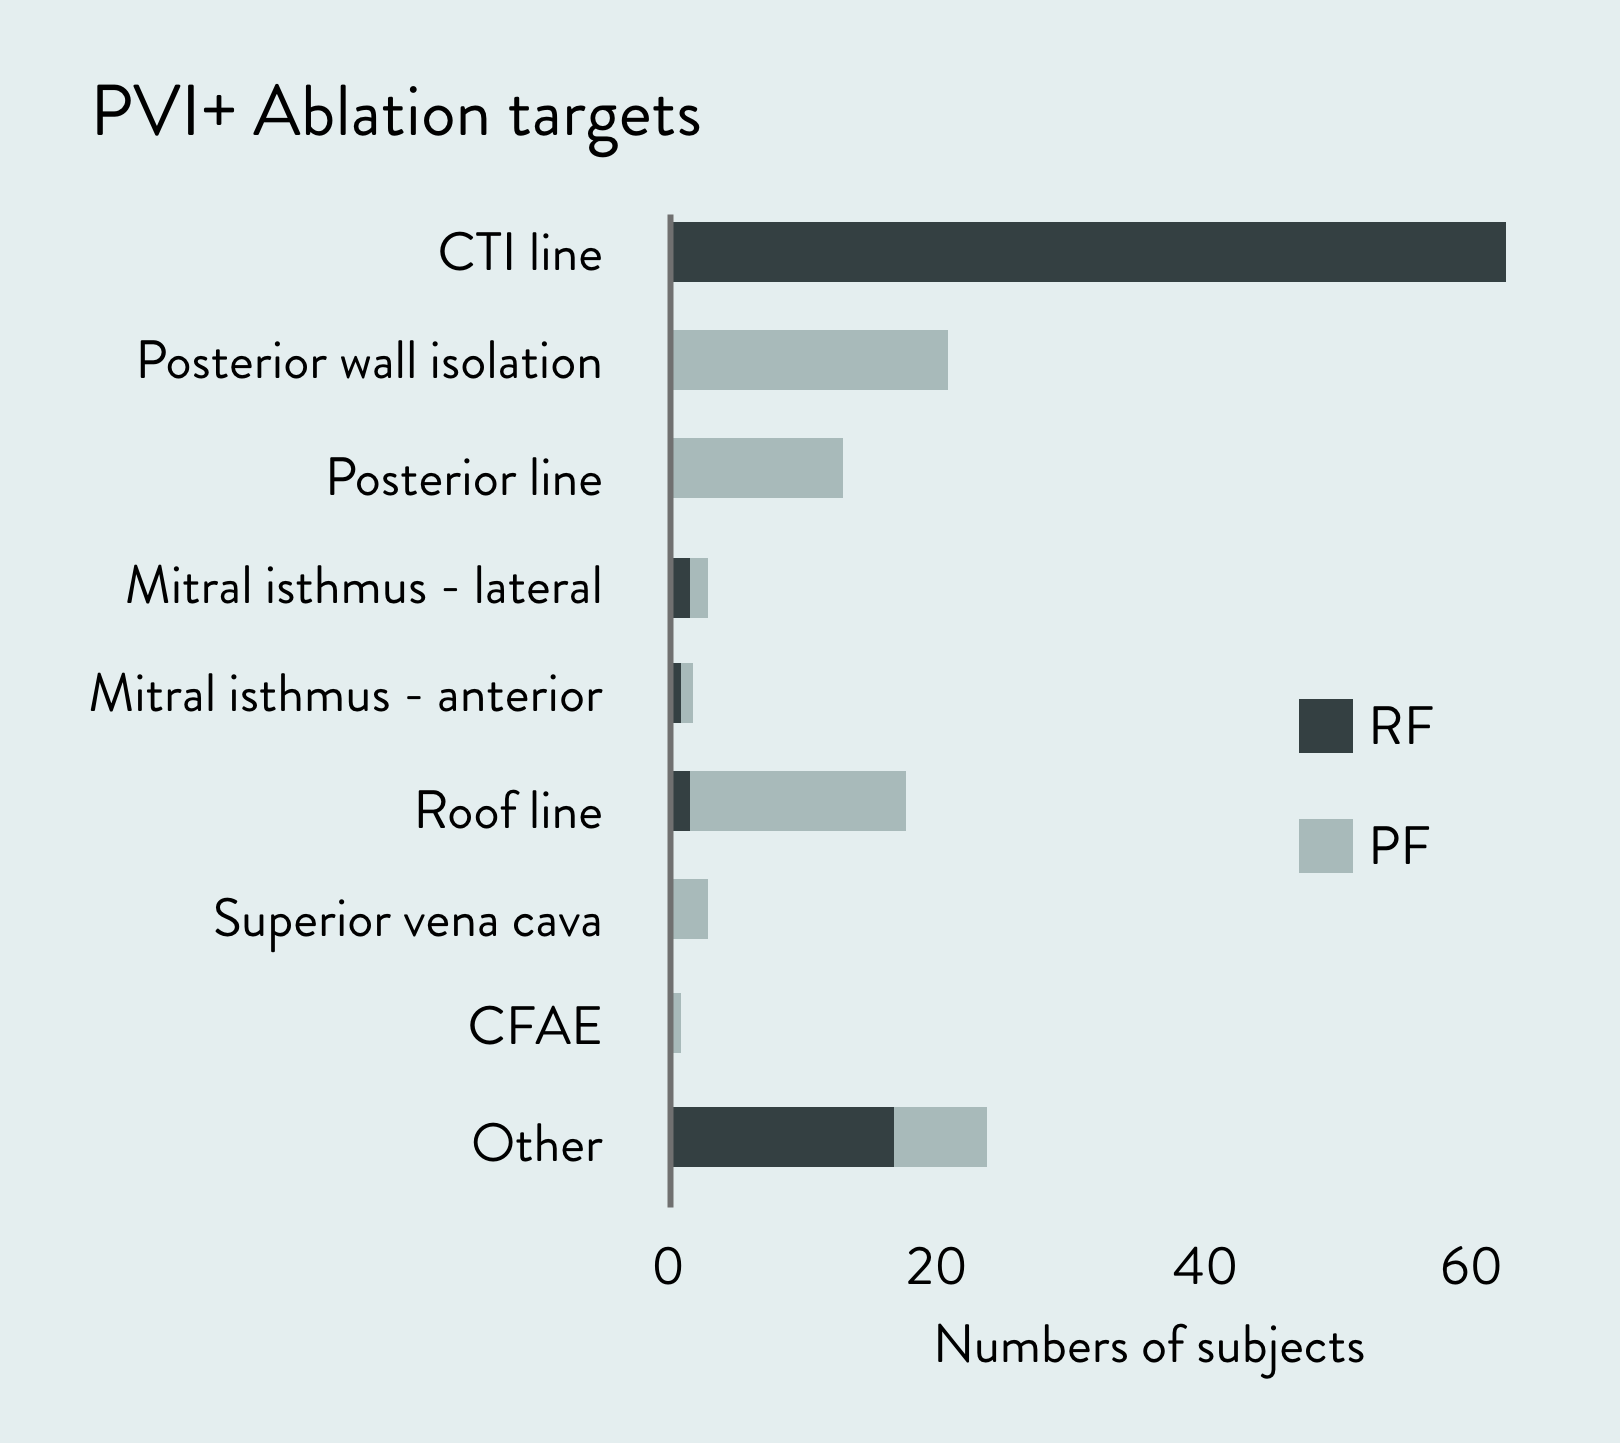
Primary safety event rate
1.8% PVI-Only subjects (4/227)
1.0% PVI+ subjects (1/97)
Lesion data: preclinical
2026 AF Symposium: Applications in porcine ventricular tissue10
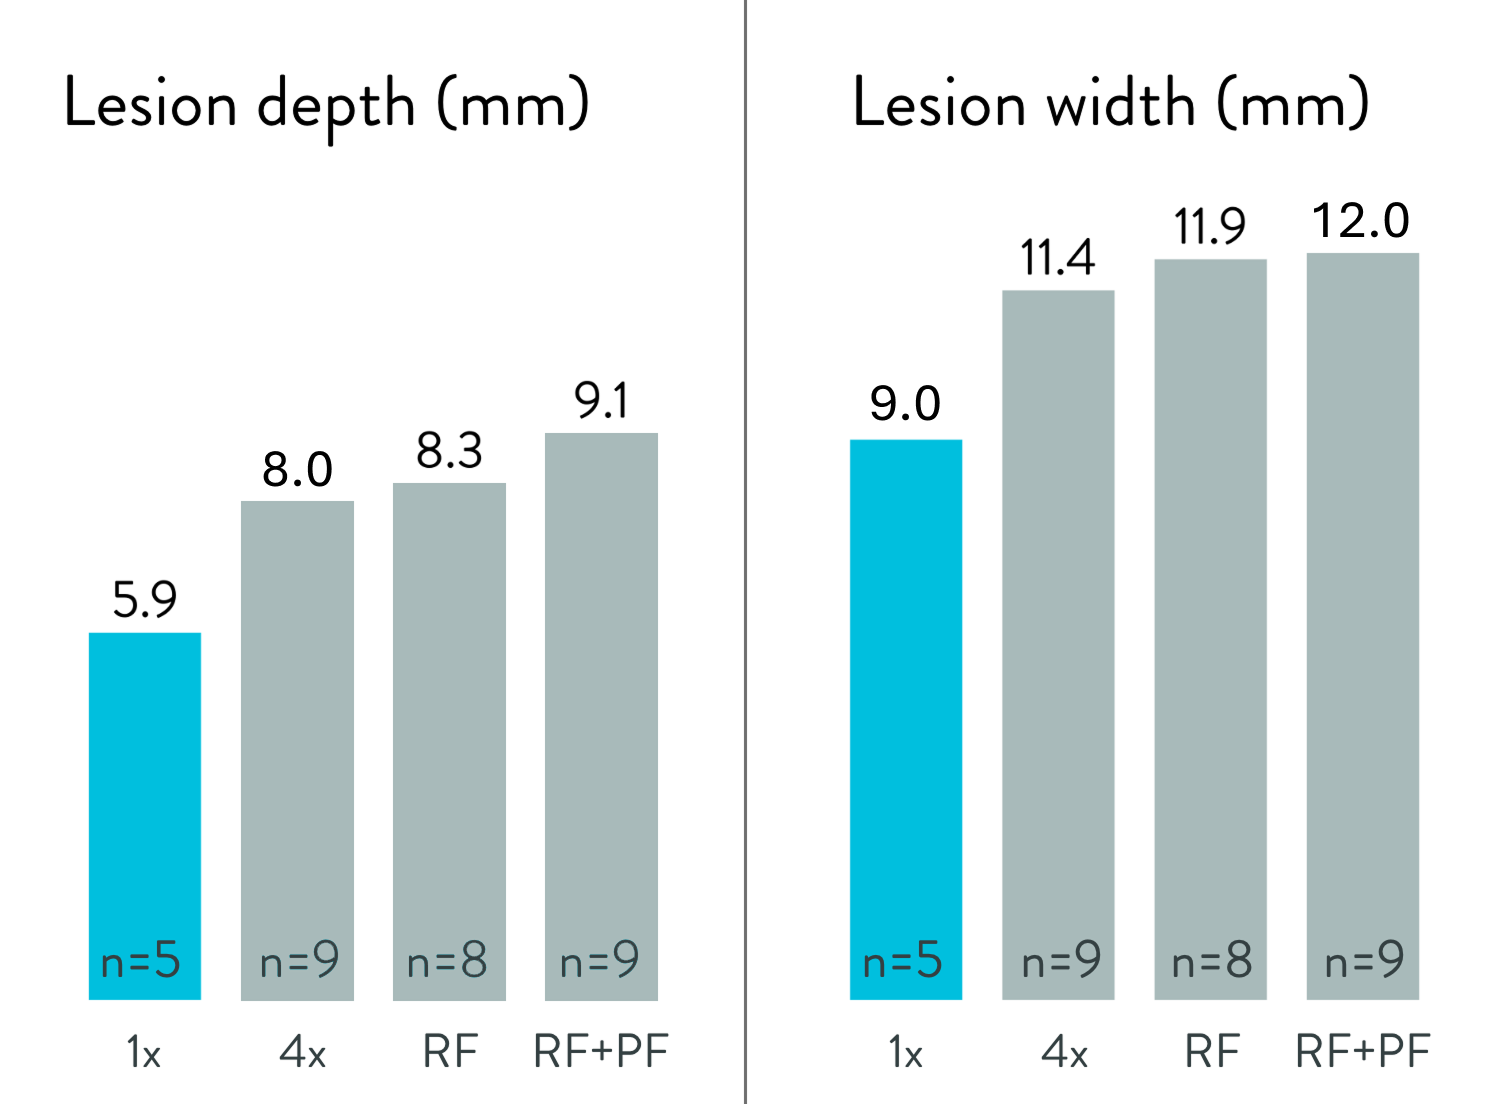
In an acute porcine model TactiFlex™ Duo demonstrated lesion depths and widths appropriate for atrial use with a single nominal PFA application, while multiple applications produced larger lesions. Lesion depth and width were not significantly different between RF alone (50 W, 20 s) and RF followed by four stacked PFA applications.10
Acute animal model (n=5) porcine ventricular Lesions created utilizing CF between 5-20 g. Applications applied as single application, stacked 4x, or sequential PF then RF.
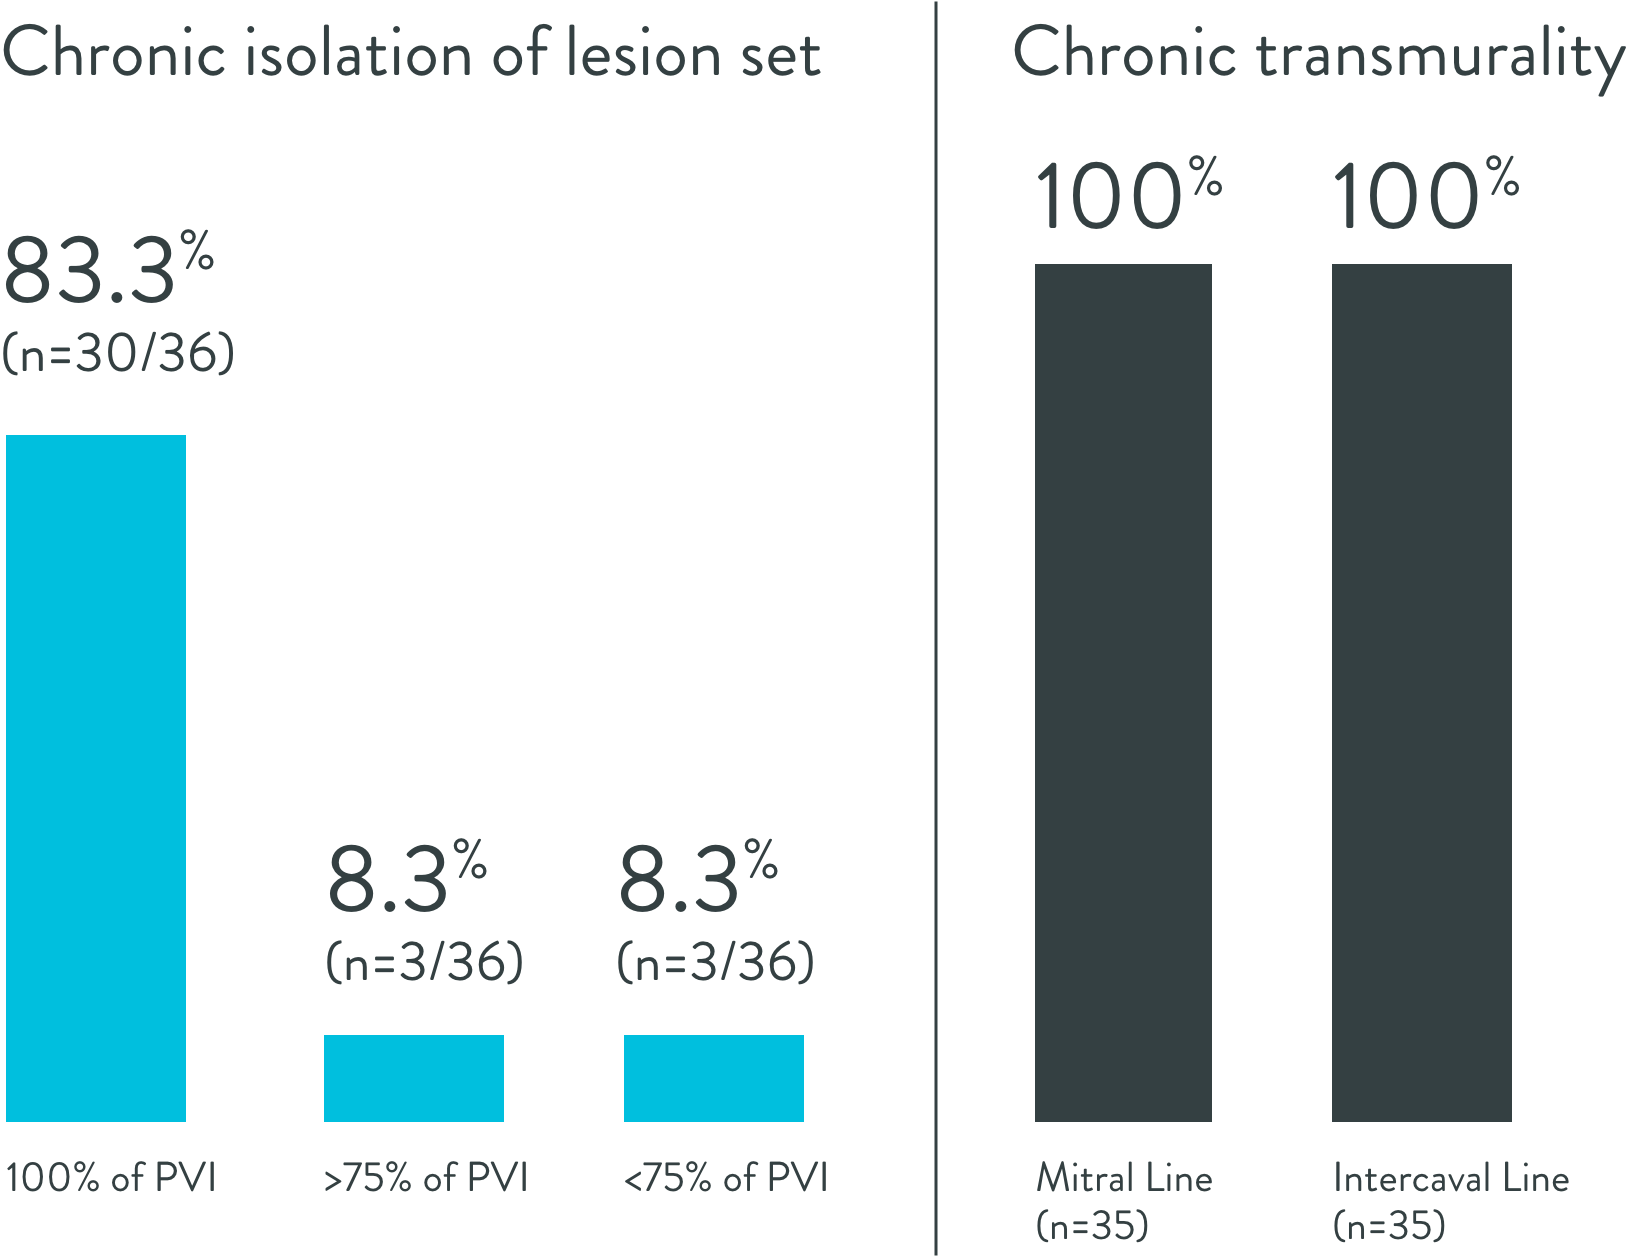
2025 HRS Abstract: Chronic Canine Safety & Efficacy7
Demonstrates the safety and effectiveness of PF only and RF+PF lesions delivered using the TactiFlex Duo catheter in creation of focal, linear, and circumferential atrial lesion sets using two distinct PFA waveforms.
* PVI confirmation after 20-minute wait period
** After 20-minute wait period and no early reconnections
*** Subset of full study cohort reported in this publication due to publication timing relative to full enrollment.
References:
- Hussein, A., Rackauskas, G., Sundaram, S., et al. (2026). Safety and effectiveness of a novel dual-energy radiofrequency/pulsed field ablation catheter: 12-month results of the FlexPulseStudy. Europace. Advance online publication. https://doi.org/10.1093/europace/euag238
- Manninger M, Scherr D, Bulava A, et al. Safety and Effectiveness of the TactiFlex Duo system: 6-month results of the FOCALFLEX Study. EP Europace 20(5), (2026). 10.1093/europace/euag108.
- Scherr, D. et al. (2025, November). General anesthesia vs. Deep sedation and Conscious Sedation in Subjects Undergoing Pulmonary Vein Isolation with a Novel Flexible-Tip Dual-Energy PF/RF Ablation Catheter [Oral Presentation]. Presented by Daniel Scherr. Asia Pacific Heart Rhythm Society (APHRS) 2025, Yokohama, Japan.
- Sanders, P. et al. (2025, November 13). Beyond Pulmonary Veins: Ablation Trends and Targets with a Novel Flexible-Tip Dual-Energy PF/RF Ablation Catheter [Oral presentation]. Presented by Prash Sanders. Asia Pacific Heart Rhythm Society (APHRS) 2025, Yokohama, Japan.
- Silberbauer, J., et al (2025, April 25). Initial Clinical Experience with the TactiFlex DUO System: Safety and Acute Results of the FOCALFLEX Study [Oral presentation]. Presented by Daniel Scherr. Heart Rhythm Society 2025, San Diego, CA.
- Lo, M., et al (2025, April 26). Acute Results of the FlexPulse IDE Trial [Poster presentation]. Heart Rhythm Society 2025, San Diego, CA.
- Koruth, J. et al. Acute and chronic pulmonary vein isolation durability and safety assessments of a focal dual-energy, flexible 4mm contact-sensing tip [Poster presentation]. Heart Rhythm Society 2025, San Diego, CA.
- Silberbauer, J., et al. (2026, February). Retrospective analysis of a PFA index and implications for lesion formation [Poster presentation]. AF Symposium 2026, Boston, MA, United States.
- Friedman, D. (2025). Development of a PFA index to guide energy delivery with a force‑sensing flexible irrigated tip catheter. European Heart Journal, 46(Suppl. 1), ehaf784.797. https://doi.org/10.1093/eurheartj/ehaf784.797
- Mittal, L., et al. (2026, February). Lesion depth saturation for sequential RF and PFA therapy using a dual‑modality focal catheter in a porcine model for atrial application [Poster presentation]. AF Symposium 2026, Boston, MA, United States.
- Sudo K, Kuroki K, Asakawa T, et al. Efficacy of a Novel Ablation Index Algorithm for Cavotricuspid Isthmus Ablation using a Flexible-Tip Ablation catheter. Journal of Arrythmia. 2026;42(3):e70378.
https://doi.org/10.1002/joa3.70378. - Lo, M. et al. (2026, October). Procedural Factors Associated with 12-Month Effectiveness Following Dual-Energy Ablation for Paroxysmal Atrial Fibrillation [Oral Presentation]. Presented by Monica Lo. Asia Pacific Heart Rhythm Society (APHRS) 2026, Busan, Korea.
- Tixier, R. et al. (2026, October). Real World Usage Trends of PI: PFA Index [Oral Presentation]. Presented by Jean-Paul Albenque. Asia Pacific Heart Rhythm Society (APHRS) 2026, Busan, Korea.
Rx Only. Brief Summary: Prior to using these devices, please review the Instructions for Use for a complete listing of indications, contraindications, warnings, precautions, potential adverse events, and directions for use.
United States: Required Safety Information
Indication: TactiFlex™ Duo Ablation Catheter, Sensor Enabled™ is indicated for use in cardiac electrophysiological mapping and ablation for the treatment of drug-refractory recurrent symptomatic paroxysmal atrial fibrillation and concomitant atrial flutter, when used in conjunction with a compatible radiofrequency (RF) or pulsed field (PF) generator and three-dimensional mapping system. Contraindications: Do not use in patients with active systemic infection, intracardiac thrombus or myxoma, prosthetic heart valves, recent ventriculotomy or atriotomy (<4 weeks), inability to receive adequate anticoagulation, or in patients for whom the specified transseptal or retrograde approaches are contraindicated. Use in the coronary vasculature is contraindicated. Warnings: Application of RF energy on the left atrial posterior wall exceeding 40 W in power, or use of contact force ≥15 g, increases the risk of esophageal perforating complications including atrio-esophageal fistula and death. Application of RF energy outside of the power and duration recommendations may increase the likelihood of steam pop occurrence. The combination of intracoronary placement of the ablation catheter and RF energy application has been associated with myocardial infarction and death. Contact force accuracy above 50 g has not been established. Increased contact force may increase the risk for perforation during manipulation of the catheter. Cases of delayed onset of atrio-esophageal fistula (AEF) have been reported in association with radiofrequency catheter ablation procedures. While rare, AEF is associated with significant morbidity and mortality. A high index of suspicion for AEF should be maintained in patients who present with symptoms including but not limited to fever, neurological deficits, hematemesis, septic shock, and dysphagia in the several weeks after a left atrial ablation procedure. Inspect tubing, connections, and saline irrigation for air bubbles prior to and throughout its use in the procedure. Air or bubbles in the saline irrigation may cause emboli, potential injury, or fatality. To avoid thromboemboli, intravenous heparin should be used when entering the left heart during ablation. Patients undergoing septal accessory pathway ablation are at risk for complete AV block which requires the implantation of a permanent pacemaker. Permanent pacing may be required in patients who experience inadvertent complete AV block as a result of RF ablation. Implantable pacemakers and implantable cardioverter/defibrillator (ICDs) may be adversely affected by RF or PFA current. It is important to: have temporary external sources of pacing and defibrillation available during ablation, temporarily reprogram the pacing system to minimum output to minimize risk of inappropriate pacing, exercise extreme caution during ablation when in close proximity to atrial or ventricular permanent leads, program the ICD to the OFF mode during the ablation procedure, perform complete implantable device analysis on all patients after ablation. Take precautions to avoid injuring the phrenic nerve, including pacing to identify the proximity of the nerve, and, when using RF, appropriately reducing power. Caution should be taken when placing lesions in the proximity of the specialized conduction system. Collateral anatomical structures need to be considered (e.g. phrenic nerve, coronary arteries and native conduction system) while manipulating catheters and prior to ablation. PF energy should not be applied to the cavotricuspid isthmus. Ablations in areas adjacent to the coronary arteries may lead to coronary artery spasm and/or injury, and the resulting myocardial injury may be fatal. Precautions: Use the catheter only in a fully equipped electrophysiology laboratory. It is recommended that the laboratory should include corresponding equipment including, but not limited to, fluoroscopy, stimulator, recording, defibrillator or ultrasound/intracardiac echocardiography (ICE) units. The PFA therapy should be delivered in accordance with Therapy Delivery Parameters. The first application of PFA will likely result in a significant reduction of amplitude of PV potentials recorded from the electrodes on the catheter. Do not use this as an immediate indication that no further ablation is necessary. During treatment with the catheter, ensure there is no possibility of contact with the electrodes or guidewire from another catheter. Always straighten the catheter tip before insertion or withdrawal. If irrigation flow is interrupted, immediately inspect and re flush the catheter outside of the patient. Re-establish irrigation flow prior to placing catheter in the body. Irrigated ablation systems have been shown to create larger lesions than standard radiofrequency ablation catheters. Be careful when ablating near electrically vulnerable, thin walled, or other arterial structures. Potential Adverse Events: Potential adverse events include, but are not limited to, death, stroke, transient ischemic attack (TIA), atrio-esophageal fistula (AEF)/esophageal injury, phrenic nerve injury/diaphragmatic paralysis, and serious cardiovascular complications including cardiac tamponade, cardiac perforation, myocardial infarction, heart block requiring permanent pacemaker implantation, pulmonary vein stenosis, thromboembolism, and major bleeding or vascular access complications. Refer to the Instructions for Use for a complete list of adverse events.
MAT-2626033 v10.0